


Pain when carrying weights or exerting strength

Pain when carrying weights or exerting strength
Gym goers or sports people commonly face the problem of shoulder pain when carrying weights or exerting strength. There are a variety of conditions and injuries which may cause such pain.
The location of the pain may give some clue about the condition. For example, if it is at the top of the shoulder, it may be an Acromio-Clavicular Joint (ACJ) issue. If it is at the front of the shoulder, it may be a Labrum issue.
Pain during exertion, but no pain if not exerting
Such pain is not uncommon, and may lull the person into a false sense of security. This is because an injury may already have been sustained that, while it may not cause pain during normal activities, may progress and degenerate over time, such that it may begin to cause pain during normal activities in time to come.
If one has rested a few weeks, and then attempted return to exercise but the pain is still present, it is advisable to have the condition examined by a specialist.
What could be the causes?
There are a wide variety of causes that cause exertional pain. These include:
– Acromio-Clavicular Joint (ACJ) arthrosis
– Impingement
– Labrum tears (a subtype of which is a SLAP tear)
– Biceps tendinitis
– Subscapularis tear
Treatment for each of these conditions do differ. Therefore, it is important to undergo a physical examination by a Shoulder specialist to diagnose the condition. Xrays and MRI are also commonly ordered to evaluate the internal condition. Only after an accurate diagnosis has been made, can appropriate treatment be started.
Frequently Asked Questions
Find quick answers to common queries, designed to help you navigate
your orthopaedic care journey with ease.
You can come see us without having to obtain any referral letters first.
The exception is if you are using a corporate insurance plan, as some corporate insurers require you to see a family doctor on your panel first, and ask for a referral letter to us.
Yes, but it can take one to three years without treatment. Early intervention shortens recovery and reduces the severity of your symptoms. Some patients are left with residual stiffness even after the condition resolves.
Starting frozen shoulder treatment early gives you the best chance of a faster recovery. For most patients, a corticosteroid injection combined with physiotherapy offers the most effective improvement. In more advanced cases, hydrodilatation or arthroscopic release may be more appropriate.
Yes, physiotherapy is one of the main pillars of frozen shoulder treatment. A structured programme of manual therapy and stretching can meaningfully improve range of motion, particularly in the frozen and thawing stages. How consistently you do your home exercises plays a significant role in how quickly you recover.
If your shoulder has been stiff or painful for more than two to three weeks without improvement, get it assessed. Night pain, difficulty reaching behind your back, or restricted overhead movement all warrant specialist review. People with diabetes or thyroid conditions should seek assessment promptly.
Yes. A corticosteroid injection reduces inflammation and pain, making physiotherapy more effective. Hydrodilatation is another option for patients who have not responded to standard injections alone.
Frozen shoulder surgery is considered when pain persists for several months and conservative treatments have not produced adequate improvement. Arthroscopic capsular release is a keyhole procedure that removes the thickened tissue restricting your shoulder. Most patients experience meaningful improvement in pain and mobility in the weeks that follow.
Recurrence in the same shoulder is uncommon. However, some patients develop it in the other shoulder at some point. The second episode does not always follow the same severity or timeline as the first.
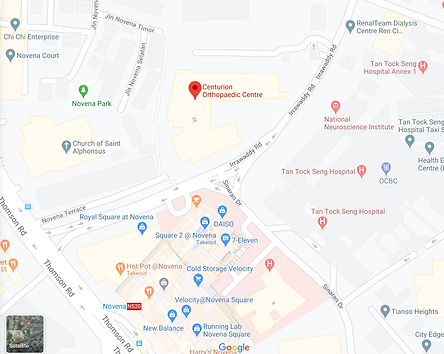
Centurion Orthopaedic Centre
38 Irrawaddy Road
Mt Elizabeth Novena Hospital Specialist Centre #07-40
Singapore 329563